Where Can Trans People Get Support in the UK?
Specialist sexual health services, national organisations and local groups, most of which are free and none of which require a referral.
By Bareback Guide
25 Aug 2026

Trans people are largely absent from the research that sexual health guidance is built on, and the practical questions get answered badly as a result. These guides cover PrEP alongside hormone therapy, screening based on the anatomy you have, post-surgical sex and finding an affirming clinic.
Specialist sexual health services, national organisations and local groups, most of which are free and none of which require a referral.
Block early, report properly and set terms before meeting. Being wanted for a category is not the same as being wanted.
Ask before you go, use specialist services where they exist, and remember that sexual health services are open access everywhere.
The same ones, on the basis of what you do rather than how you are registered. Eligibility is frequently applied too narrowly.
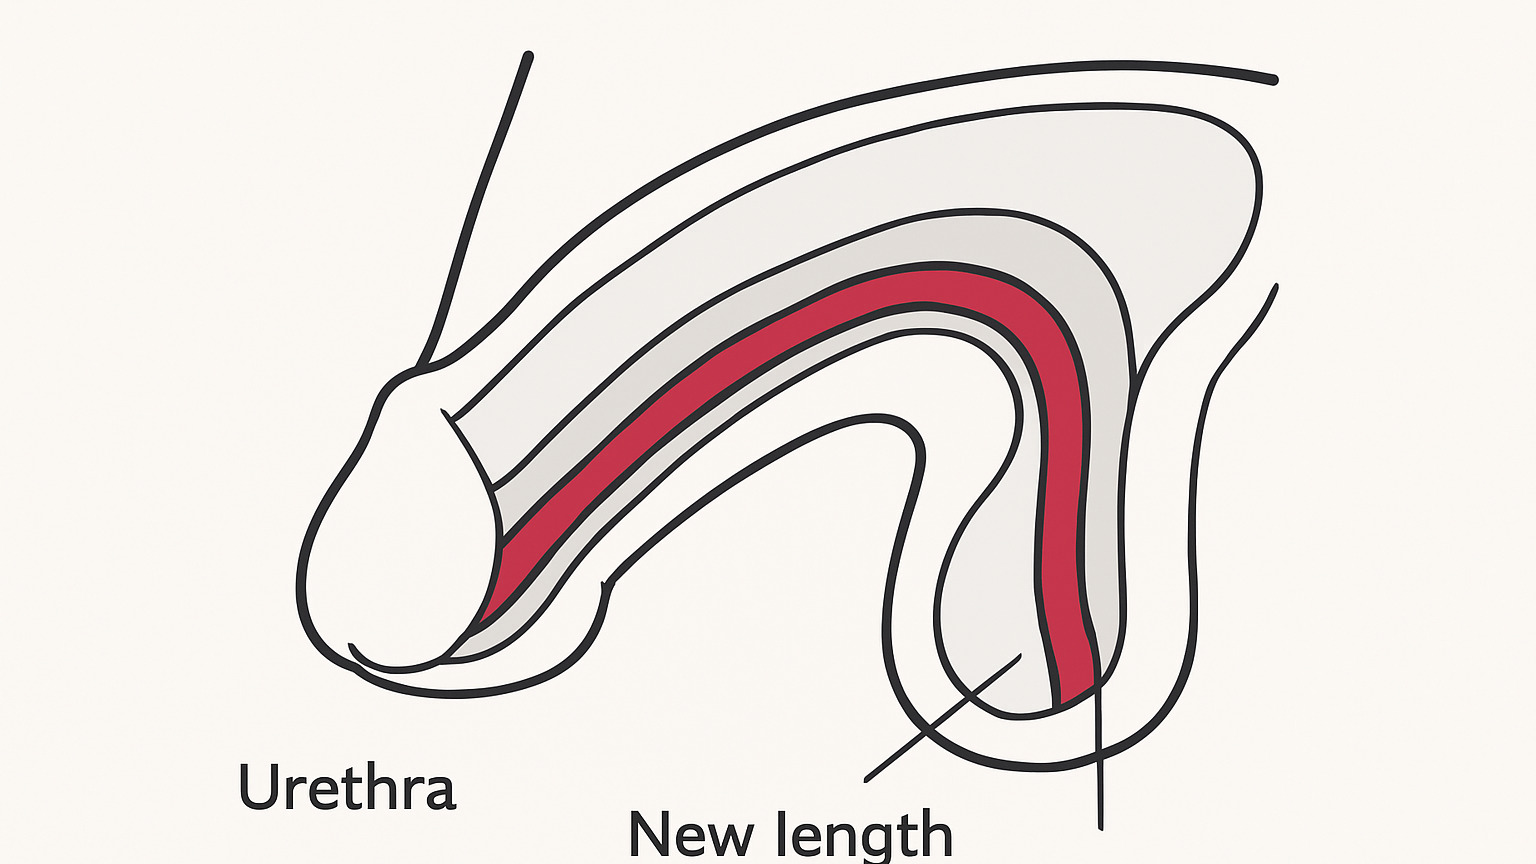
Mainly the urethra, if it was lengthened. That is where the complications sit and where the testing changes.
It needs lubricant, dilation and its own swabs. Infections happen there and the site is frequently left out of testing.
No. Pregnancy is possible on testosterone even without periods, and the belief that it is not is widespread and consequential.
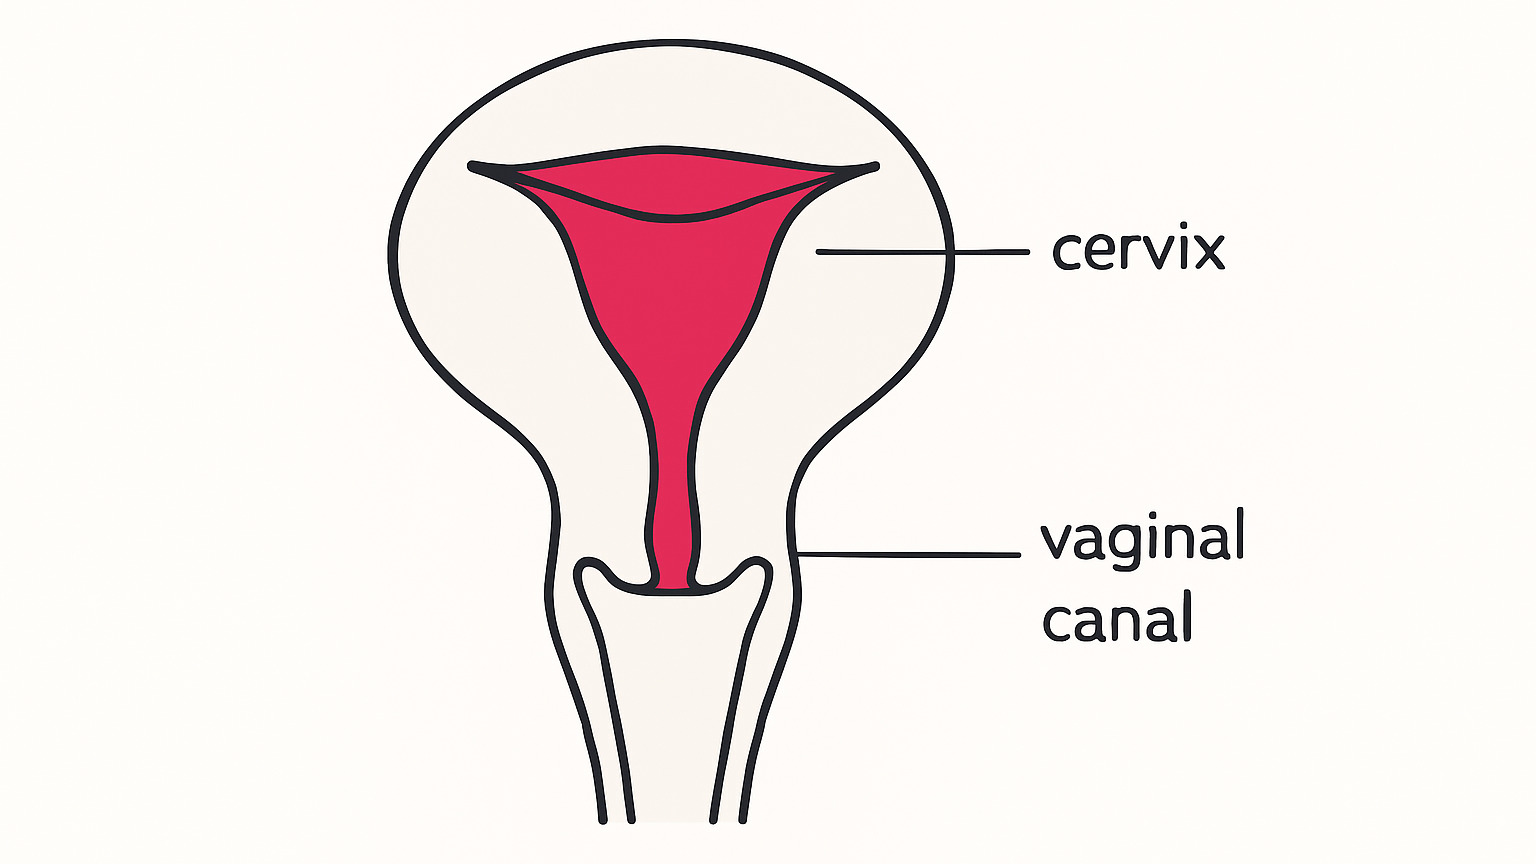
If you have a cervix, yes. And if you are registered male with your GP, the invitation will not arrive on its own.
It thins and dries frontal tissue, which makes tearing more likely. That is a manageable effect rather than a reason to stop.
Every site you use for sex, swabbed individually. Assumptions about which sites those are cause most of the missed infections.
Daily, in most cases. The shortcut schedule has not been established for frontal or neovaginal sex and should not be assumed.
No, in either direction. It is the most common reason trans people avoid PrEP and it is not supported by the evidence.